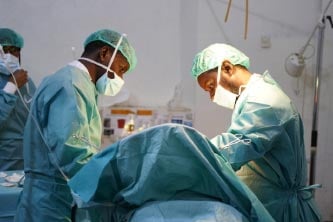



Bunia, Democratic Republic of Congo – As the Ebola disease outbreak, caused by the Bundibugyo virus, continues to spread in the Democratic Republic of Congo (DRC), Médecins Sans Frontières (MSF) and Epicentre, MSF’s epidemiological research centre, are launching a vaccination study, BRAVO.1 The significant study will follow frontline workers in the Ebola response over time to assess the effect of the ERVEBO vaccine. The study is integrated into the Ministry of Health-led outbreak response. No vaccine or treatment specifically targeting Bundibugyo virus is immediately available.
Conducted with the Ministry of Health, Africa CDC, the Congolese National Institute for Biomedical Research (INRB), and scientific partners, the study will document and evaluate the use of ERVEBO, the only Ebola vaccine currently available at scale. The vaccine has a well-established safety profile and has been widely used in DRC. However, it was developed and licensed for the Zaire virus of Ebola disease, not Bundibugyo virus, which is driving the current outbreak.
“Although ERVEBO was not originally developed to protect against Bundibugyo, preliminary data suggest that it may offer some degree of protection against the virus,” says Dr Guyguy Manangama, epidemiologist and deputy director of operations at MSF. “In a race against time such as the one the DRC is currently facing, we must use every tool available to us.”
Even partial protection could help reduce severe illness and deaths... That is precisely the purpose of BRAVO.Dr Guyguy Manangama, epidemiologist and deputy director of operations at MSF
“Even partial protection could help reduce severe illness and deaths,” says Dr Manangama. “However, these potential benefits must be demonstrated scientifically. That is precisely the purpose of BRAVO.”
Launched on 19 September at the World Health Organization (WHO)-run training centre for health workers in Bunia, the study will run for a period of nine to 12 months. This will include three months dedicated to vaccination and a minimum of six months of participant follow-up. It will target 20,000 frontline workers in Ituri and North Kivu provinces, a group at particularly high risk of exposure to the virus and essential to the outbreak response. The study will generate real-world data on the use of the ERVEBO vaccine and its potential effectiveness in the current outbreak context.
Several vaccines specifically targeting Bundibugyo virus are under development and may become available in the coming months. Continuing and accelerating this research remains essential. In the meantime, ERVEBO is being offered as an interim measure because of its established safety profile and its approval by several leading regulatory authorities, including the United States Food and Drug Administration (FDA), the European Medicines Agency, and WHO.
Participation in BRAVO and vaccination are entirely voluntary. Vaccination is an additional protective measure; it does not replace proven infection prevention and control measures. All frontline workers must continue to use protective equipment, follow safe-care procedures, and report symptoms quickly.
“It is important to stress that this vaccine will not end the current outbreak,” says Dr Manangama. “However, it may offer additional protection to those most exposed, and help strengthen the response alongside other essential interventions.”

DRC Ebola outbreaks
Assuming the Ebola disease outbreak in DRC is under control would be a mistake
Press Release
18 Sep 2026

DRC Ebola outbreaks
100 days of Ebola disease outbreak: Faster and more flexible response needed to curb deadly spread in DRC
Press Release
21 Aug 2026
Democratic Republic of Congo
Other health emergencies must not be neglected in eastern DRC
Project Update
14 Aug 2026